
CBD and Chronic Pain: What the Evidence Actually Shows
Written and medically reviewed by Gregory A. Smith, M.D.Medically reviewed · Updated
Which cannabinoid, which formulation, what route, and for how long? Those questions matter when discussing CBD and chronic pain with a clinician.
Why chronic pain deserves a careful conversation
In 2023, 24.3% of U.S. adults experienced chronic pain, including 8.5% with high-impact chronic pain that frequently limited life or work activities. The high-impact group is part of the chronic-pain group, not an additional group to add to it. Chronic pain in this survey meant pain on most days or every day during the previous three months.
I have been treating patients with chronic pain for 30 years. In my clinical experience, the cannabinoid or combination of cannabinoids, formulation, dose, route, and duration all deserve attention. A retail label alone cannot answer whether a particular product belongs in an individual patient’s care plan.
Patients may already be using anti-inflammatory drugs, steroids, opioids, or other treatments. That existing care needs to be reviewed before adding a cannabinoid. Clinical experience can guide questions, but it does not replace controlled research or establish that CBD works for every type of chronic pain.
CDC: Chronic Pain and High-impact Chronic Pain in U.S. Adults, 2023What the trials show
A systematic review of 36 randomized trials involving 4,006 people with chronic non-cancer pain found a small average reduction in pain with cannabinoids compared with placebo, about 0.68 points on a 0–10 scale at two to eight weeks. The review included smoked cannabis, sprays, and oral cannabinoids. It was not a review of CBD alone. Evidence was moderate at two weeks and less certain later; non-serious adverse events were more common with cannabinoids.
The 2024 AHRQ living review also distinguished products by their THC-to-CBD ratio and emphasized the limits of short-term evidence. An updated Annals of Internal Medicine review of 25 trials involving 2,303 participants found small improvements with some THC-containing products, alongside increased dizziness, sedation, and nausea. Low-THC-to-CBD products may not improve outcomes.
These findings should not be presented as proof that a CBD capsule treats chronic pain. The formulation, condition, comparison group, and outcome all matter. Limited benefit in a trial also cannot automatically be explained by saying the dose was too low.
Cannabinoids in Chronic Non-Cancer Pain: A Systematic Review and Meta-Analysis.AHRQ: Living Systematic Review on Cannabis and Other Plant-Based Treatments for Chronic Pain, 2024 updateCannabis-Based Products for Chronic Pain : An Updated Systematic Review.Why formulation and route change the result
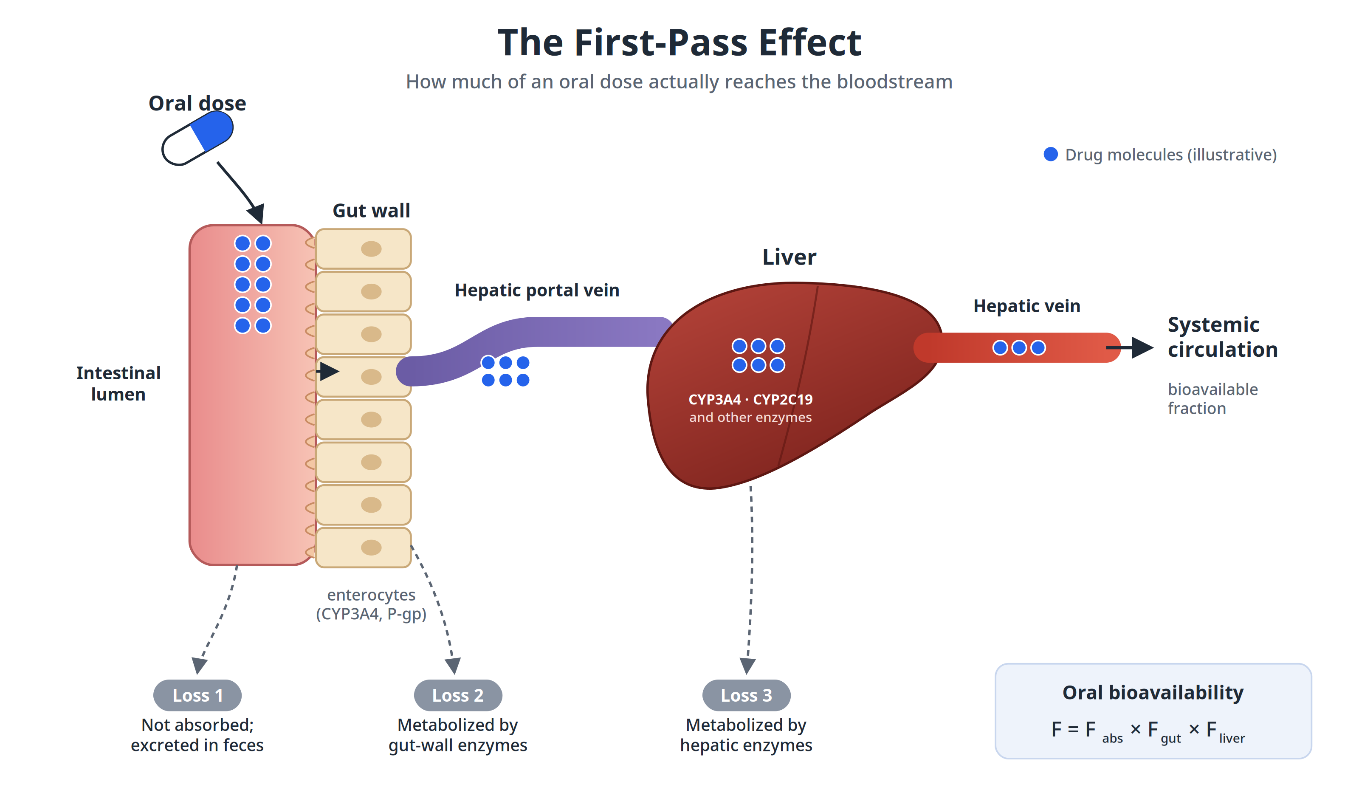
An oral dose does not reach the bloodstream unchanged. Some is not absorbed, and some is metabolized in the gut wall and liver before reaching systemic circulation. This is part of the first-pass effect. CBD’s low water solubility, formulation, food, and route of administration can affect exposure.
The diagram illustrates this process. Its dots are illustrative, not a measured absorption percentage for every medication or CBD product. Different medicines and formulations have different bioavailability.
Food can change exposure to prescription cannabidiol substantially, which is why its prescribing information advises consistent administration in relation to meals. A cream, a swallowed capsule, and a product placed under the tongue should not be assumed to deliver an equivalent dose. Ask your clinician about the specific product rather than increasing the amount to compensate for an assumed absorption percentage.
Why dose needs individual clinical review
In my practice, I consider the patient’s history, existing treatments, and formulation instead of choosing a dose from the retail label. Someone with long-standing pain and previous opioid treatment needs an individualized review, not a promise about a particular capsule strength.
A review of lower oral CBD doses found inconsistent evidence for chronic pain and called for stronger trials. Research doses and a clinician’s experience with selected patients are not instructions for self-treatment. There is no universal CBD dose established for chronic pain, and more is not automatically better.
Other cannabinoids and terpenes change the formulation, so research on one combination cannot establish the effects of another. Any decision to start or adjust a product should be made with the clinician who knows your medication list and health history.
The safety and efficacy of low oral doses of cannabidiol: An evaluation of the evidence.Safety questions worth asking before your first dose
Safety is always the primary concern. I assess tolerability before considering changes in a patient’s plan. A tolerated first dose does not rule out later side effects, medication interactions, or liver-enzyme changes.
CBD affects enzymes involved in medication metabolism. Prescription cannabidiol carries warnings about liver injury and sedation, and FDA investigators have also reported liver-enzyme elevations in some healthy adults in a consumer-dose study. “Natural” does not mean there is no chance of harm.
This is why, in my opinion, medical CBD should be monitored by a healthcare provider educated in cannabinoid medicine. Bring every prescription, over-the-counter medicine, supplement, and product label to the review. Do not stop or change prescribed pain medicines on your own.
FDA: Epidiolex prescribing information, revised June 2025FDA: CBD safety in a randomized trialRead the CBD drug-interaction guideWhat a supervised approach looks like here
The five steps are clinical review, product and route selection when appropriate, an individualized starting plan, tracking pain and function, and follow-up with adjustment. The initial review may also lead to a decision not to use CBD.
I want patients to understand which cannabinoid or combination is being considered, why a particular formulation was selected, what benefit would count as meaningful, and what would be a reason to stop. Tracking daily function as well as pain gives the follow-up conversation more useful information.
Product quality and knowledgeable clinical guidance matter, but they do not guarantee relief. If a product is not helping or causes unwanted effects, the plan needs reassessment. A supervised approach makes room for uncertainty and keeps the patient’s existing care at the center of the decision.
Common questions
How long before I know if it is working?
Agree with your clinician on what to track and when to reassess. Pain, daily function, and unwanted effects all matter. A study’s follow-up period is not a guarantee about when an individual will benefit.
Can I use CBD with my current pain medication?
Have your prescriber or pharmacist review the exact medicines, doses, and CBD formulation before combining them. Do not stop or change prescribed pain treatment on your own.
Will CBD make me high?
CBD itself is not intoxicating in the way THC is, but products may also contain THC and CBD can cause drowsiness. Check the product label and batch report with your clinician.
Should I choose a capsule or a cream?
They are different routes of exposure and are not interchangeable. Ask your clinician which formulation, if any, fits your health history and goals.
Does more CBD always work better?
No. More can increase exposure, interactions, and unwanted effects without providing more benefit. There is no universal CBD dose established for chronic pain; dosing decisions belong with your treating clinician.
Sources
- CDC: Chronic Pain and High-impact Chronic Pain in U.S. Adults, 2023
- Cannabinoids in Chronic Non-Cancer Pain: A Systematic Review and Meta-Analysis.
- AHRQ: Living Systematic Review on Cannabis and Other Plant-Based Treatments for Chronic Pain, 2024 update
- Cannabis-Based Products for Chronic Pain : An Updated Systematic Review.
- The safety and efficacy of low oral doses of cannabidiol: An evaluation of the evidence.
- FDA: Epidiolex prescribing information, revised June 2025
- FDA: CBD safety in a randomized trial
This page is educational and is not medical advice. It does not claim that cannabidiol diagnoses, treats, cures, or prevents any disease. Cannabidiol can interact with prescription medications. Talk with a licensed clinician who understands cannabinoid medicine before starting any CBD product, and do not stop or change a prescribed medication on your own. These statements have not been evaluated by the Food and Drug Administration.
Bring your questions to a provider
Red Pill Medical products are available through our network of clinicians and independent pharmacies. Start with a short intake, then schedule your required video consultation so a professional can review your health history and medication list. Bring your product label and questions to discuss with your clinician.
Read product lab reportsExplore productsAll education guides